Medical review: Estexper Medical Editorial Team
Hair transplantation can be an effective option for carefully selected people with stable, permanent hair loss. However, not every type of hair loss is suitable for surgery. Patients with alopecia areata or diffuse unpatterned alopecia, often called DUPA, require particular caution because the condition may affect both the recipient area and the proposed donor area.
In Short
- Hair transplantation is generally unsuitable when alopecia areata is active, progressive or uncertain because the immune process may affect transplanted follicles and outcomes are unpredictable.
- Confirmed DUPA is usually a poor indication because miniaturization may involve the occipital donor area, leaving no reliably stable donor supply.
- In selected people with a remote history of alopecia areata, surgery may be discussed after prolonged stability, but recurrence and graft loss remain possible.
- Suitability depends on an accurate diagnosis, full-scalp and donor-area assessment, and review by a qualified physician—not the country where surgery is performed.
For international patients considering a hair transplant in Turkey, the country where surgery is performed does not change the underlying biology of these conditions. Suitability depends on an accurate diagnosis, disease activity, the quality and stability of the donor area, and an assessment by a qualified physician. In many cases, medical evaluation and monitoring are more appropriate than immediate surgery.
What is alopecia areata?
Alopecia areata is an immune-mediated hair-loss disorder. The immune system can target hair follicles, causing hair to fall out in round or irregular patches. The condition may be limited to a few areas or may affect a larger part of the scalp and body. It can also relapse after a period of improvement.
This pattern is different from typical androgenetic or pattern hair loss, where hair follicle miniaturization usually follows a more predictable distribution. In alopecia areata, the disease process itself may remain active even when hair loss appears to have stabilized temporarily.
Because transplanted follicles may also be affected by the immune process, transplantation cannot reliably remove the risk of future hair loss. Surgical trauma may also potentially trigger recurrence or worsening in some individuals. For these reasons, active alopecia areata is generally considered a contraindication or a strong reason to avoid hair transplantation.
What is diffuse unpatterned alopecia?
Diffuse unpatterned alopecia is a form of diffuse follicular miniaturization that does not follow the usual pattern of hair loss. Unlike typical pattern hair loss, DUPA may involve the frontal, temporal, parietal and occipital scalp. This is important because the occipital region is often selected as the donor area for transplantation.
In a person with confirmed DUPA, the presumed donor zone may contain many miniaturized or vulnerable follicles. Removing these follicles and transplanting them elsewhere may not provide a durable result. There may also be no clearly stable area from which enough grafts can be safely harvested.
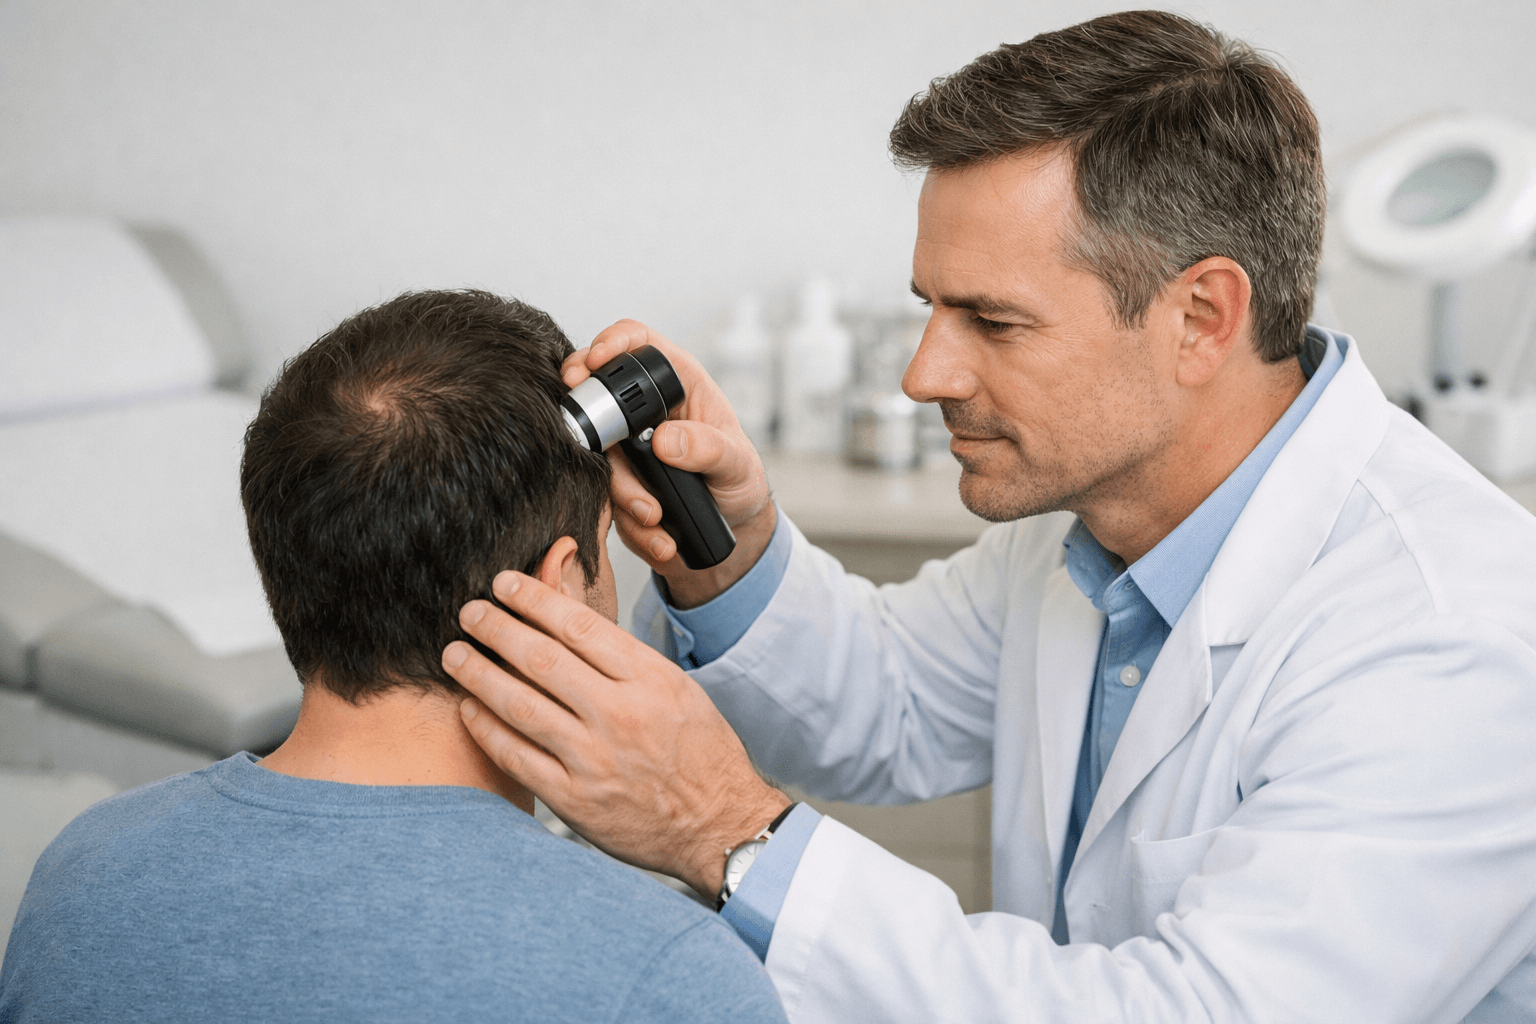
DUPA can be overlooked if the occipital scalp is assumed to be permanent without detailed examination. Clinical assessment and trichoscopy comparing the vertex and occipital regions can help identify donor-area involvement. In selected situations, a physician may consider additional objective assessment, such as a biopsy, when the diagnosis remains uncertain.
Is hair transplantation suitable for alopecia areata?
Usually, hair transplantation is not suitable when alopecia areata is active, progressive or diagnostically uncertain. The main concerns include:
- The autoimmune process may affect transplanted follicles.
- Surgery may be followed by recurrence or worsening of hair loss.
- The response to surgery is difficult to predict.
- The available evidence is limited and is based mainly on case reports and expert opinion rather than robust clinical trials.
- Hair loss may continue in areas that were not treated, making the overall result appear uneven over time.
Published expert guidance has discussed transplantation only for highly selected patients with a previous history of alopecia areata who have experienced prolonged clinical stability. A period of at least two years without active disease is commonly cited in expert discussions, but this is not a guarantee that the disease will not recur or that transplanted follicles will remain unaffected.
A history of alopecia areata should therefore be disclosed during consultation, even if the scalp currently appears normal. The physician may need to review the pattern and timing of previous episodes, treatments, regrowth, nail changes or other symptoms, and any recent signs of activity.
Is hair transplantation suitable for DUPA?
Confirmed DUPA is generally considered a poor indication for hair transplantation. The central issue is donor reliability. A transplant depends on harvesting follicles that are expected to remain stable after relocation. If miniaturization affects the occipital or other donor regions, that assumption may not be valid.
FUE or another harvesting technique cannot make an unstable donor area permanent. If follicles are already miniaturized throughout the scalp, harvesting them may produce limited coverage while reducing the remaining donor reserve. Transplanted follicles may also continue to miniaturize if they are biologically susceptible.
For this reason, a patient should not be classified as a transplant candidate based only on the appearance of the hairline or a quick visual inspection of the back of the scalp. A detailed examination of the entire scalp is important before any decision is made.
How is candidacy assessed?
Assessment should begin with confirming the diagnosis. Diffuse shedding, patchy loss and generalized thinning can have different causes, and these causes may require different management. A consultation should consider the medical history, family history, onset and progression of hair loss, previous diagnoses, medications and any symptoms affecting the scalp.
The physician may examine the scalp clinically and use trichoscopy to assess hair shaft thickness, follicular units, miniaturization and signs of disease activity. In suspected DUPA, the donor region should be evaluated rather than automatically treated as permanent. Comparing the vertex and occipital areas can be particularly useful.
When the diagnosis is unclear, additional investigations may be considered by the treating physician. The purpose is not simply to estimate how many grafts could be removed, but to determine whether the donor supply is stable enough for surgery and whether the underlying condition is medically controlled.
A qualified physician should also discuss expectations. A transplant does not treat the immune mechanism of alopecia areata, and it cannot correct the underlying diffuse miniaturization of DUPA. The decision should be based on long-term risk, not only on the current appearance of the scalp.
What preparation may be needed?
Patients should arrange a proper medical consultation before booking surgery. For international patients travelling to Turkey, a remote assessment may be useful as an initial step, but it should not replace an in-person examination when the diagnosis or donor quality is uncertain.
Before surgery, patients should provide clear information about:
- Previous episodes of patchy or diffuse hair loss
- Periods of regrowth or relapse
- Any diagnosis of alopecia areata or another scalp disorder
- Previous scalp biopsies, trichoscopy reports or medical treatments
- Recent changes in shedding, density or scalp symptoms
If active disease, progression or diagnostic uncertainty is present, postponing surgery may be the safer decision. Medical stabilization and longitudinal monitoring are generally more appropriate in these circumstances. The exact plan should be determined by a dermatologist or hair-restoration physician who can assess the individual directly.
What happens if surgery is considered?
If a patient with a remote history of alopecia areata is carefully selected after prolonged stability, the physician should explain that the evidence remains limited and that surgery carries uncertainty. The donor area must be sufficiently reliable, and the proposed recipient area should not show signs suggesting active disease.
The surgical technique does not eliminate the underlying risk. Follicular unit extraction, for example, may allow individual follicles to be harvested, but it does not prevent an autoimmune relapse or guarantee that transplanted hairs will remain unaffected. The number of grafts should be planned conservatively when donor reserves are uncertain.
Patients should receive a clear explanation of possible outcomes before consenting. These may include incomplete growth, future patchy loss, continued thinning outside the transplanted area, an uneven appearance or the need to avoid further harvesting if the donor supply becomes limited.
Recovery and aftercare
When surgery is considered appropriate, recovery instructions generally focus on protecting the recipient and donor areas while they heal. Patients should follow the clinic’s instructions about washing, touching, physical activity and follow-up. The treating team should also be informed promptly about unexpected inflammation, marked discomfort, new patches of hair loss or other changes after the procedure.
Follow-up is particularly important for patients with a history of alopecia areata or diffuse thinning. A short-term postoperative appearance cannot confirm long-term success. Ongoing monitoring may help identify recurrence, progressive miniaturization or changes in the donor area.
International patients should establish how follow-up will be managed after returning home. They should know who to contact if new symptoms appear and whether continuing assessment with a local dermatologist is recommended.
Risks of proceeding with an unsuitable diagnosis
The most significant risk is not simply a disappointing cosmetic result. If the diagnosis is missed or the donor area is unstable, surgery may use valuable follicles without providing durable coverage. This can make future treatment more difficult.
In active alopecia areata, surgery may potentially trigger or coincide with renewed disease activity. Transplanted hairs may also be targeted by the immune process. In DUPA, the transplanted follicles and the remaining scalp hair may continue to show diffuse miniaturization, making the result less predictable.
These risks are why a clinic should not promise a fixed outcome based only on photographs or a standard graft estimate. A responsible recommendation may be to delay or decline surgery when the biological indications are unfavorable.
What are the alternatives?
When alopecia areata is active, progressive or uncertain, the priority is assessment and medical management rather than transplantation. Current guidance emphasizes evidence-based treatment of the underlying condition and evaluation of disease severity. A dermatologist can discuss appropriate options based on the individual diagnosis and clinical situation.
For suspected DUPA, the first step is confirming whether the diffuse miniaturization truly affects the donor region and whether another condition could explain the thinning. Longitudinal monitoring can help determine how the scalp changes over time. If the donor area is not stable, surgery is generally not an appropriate solution.
Choosing not to undergo a transplant immediately does not mean that no further care is possible. It means that the treatment plan should address the cause of hair loss and avoid using a limited donor reserve before the diagnosis and prognosis are clear.
Does having surgery in Turkey change suitability?
Turkey is a popular destination for international hair-restoration patients, but location does not change the medical suitability of surgery. Alopecia areata remains an immune-mediated condition, and DUPA remains a disorder in which donor-area stability may be unreliable, regardless of where treatment is performed.
Patients should choose a clinic based on appropriate physician involvement, transparent diagnosis, realistic counselling and a clear follow-up plan. They should be cautious of consultations that recommend surgery without examining the donor area, dismiss a history of patchy hair loss, or guarantee permanent results.
Frequently asked questions
Can a hair transplant cure alopecia areata?
No. Hair transplantation does not treat the immune mechanism responsible for alopecia areata. Transplanted follicles may also be affected if the disease becomes active.
How long should alopecia areata be inactive before surgery?
Expert discussions commonly refer to at least two years without active disease for exceptionally selected cases. This is not a universal guarantee or a substitute for individual assessment.
Can someone with DUPA use the occipital area as a donor?
Not necessarily. DUPA can involve the occipital scalp, so the donor area must be examined carefully. Confirmed involvement usually makes transplantation inappropriate or high risk.
Is trichoscopy important before a hair transplant?
Yes. Trichoscopy can help assess miniaturization and compare the donor and recipient areas. It is especially useful when alopecia areata, DUPA or another diffuse hair-loss disorder is suspected.
Should I travel to Turkey before confirming my diagnosis?
Patients can begin with a remote consultation, but an in-person examination is important when the diagnosis, disease activity or donor quality is uncertain. Surgery should be considered only after a qualified physician has assessed these factors.
Conclusion
Hair transplantation is generally unsuitable for active alopecia areata and is usually a poor option when diffuse unpatterned alopecia affects the donor area. In selected people with a remote history of alopecia areata, surgery may be discussed after prolonged stability, but the evidence is limited and no outcome can be guaranteed.
The safest decision begins with an accurate diagnosis, full-scalp examination, trichoscopy when appropriate, and realistic discussion of long-term risks. Estexper Clinic encourages international patients to seek qualified medical assessment before arranging surgery, because the suitability of treatment depends on the individual scalp—not on the country in which the procedure is performed.
Medical References
- British Association of Dermatologists living guideline for managing people with alopecia areata 2024 — British Association of Dermatologists.
- Is Every Patient of Hair Loss a Candidate for Hair Transplant?—Deciding Surgical Candidacy in Pattern Hair Loss — Dermatologic Surgery / Thieme; indexed in PubMed and available through PMC.
- Alopecia areata: Part 2: treatment — Journal of the American Academy of Dermatology; available through PMC.
- Case Report: Paired vertex-occipital assessment reveals donor-area involvement in diffuse unpatterned alopecia — Frontiers in Medicine; indexed in PubMed and available through PMC.
- Follicular Unit Extraction (FUE) – One Procedure, Many Uses — Journal of Cutaneous and Aesthetic Surgery; available through PMC.