Medical review: Estexper Medical Editorial Team
Traction alopecia is hair loss caused by repeated or prolonged pulling on the hair and scalp. Tight ponytails, braids, extensions, weaves, locs, hairpieces and other tension-producing styles may contribute to the condition. In its early stages, traction alopecia may improve or stabilize when the pulling force is stopped. However, continued tension can permanently damage hair follicles and create areas of scarring alopecia.
In Short
A hair transplant for traction alopecia may be considered for selected patients with permanent, stable hair loss after the source of traction has stopped. A qualified physician should confirm the diagnosis, assess for active inflammation or progression, and evaluate donor hair and the scarred recipient scalp. Results in scarred areas can be less predictable than in nonscarred scalp, so surgery should be viewed as individualized reconstruction rather than a guaranteed cure.
For patients with longstanding, permanent hair loss, a hair transplant may be considered as a reconstructive option. It is not suitable for everyone, and it should not be used as a substitute for stopping the hairstyle or practice that caused the traction. The key question is whether the hair loss is permanent, stable and technically suitable for transplantation.
What Is Traction Alopecia?
Traction alopecia develops when repeated tension places stress on the hair follicles. The condition commonly affects the hairline, temples and areas exposed to tight styling, although the pattern depends on how the hair is pulled. Early traction may cause tenderness, itching, broken hairs or thinning. Some people notice short hairs around the hairline, while others may develop a gradually receding edge.
When the tension continues, follicular damage may become irreversible. The affected skin can become smooth and shiny, with fewer visible follicular openings. At this stage, the hair loss may be classified as scarring or permanent traction alopecia. The earlier the cause is recognized and removed, the greater the opportunity to prevent further follicular destruction.
Can a Hair Transplant Treat Traction Alopecia?
A hair transplant may restore hair to selected areas of permanent traction alopecia. During the procedure, healthy hair follicles are taken from a suitable donor area and placed into the area affected by hair loss. The aim is to improve coverage and the visual appearance of the hairline or other depleted regions.
However, transplantation does not treat the underlying cause of traction alopecia. If tight hairstyles, extensions or other sources of pulling continue, the transplanted and existing hairs may remain vulnerable to further trauma. A consultation should therefore address both the possibility of restoration and the long-term changes needed to protect the scalp.
Evidence specifically concerning hair transplantation for traction alopecia is limited. Published information includes reviews, case reports and evidence from the broader field of scarring alopecia rather than large, high-quality clinical trials. For this reason, results and treatment plans cannot be guaranteed, and suitability must be determined individually by a qualified physician.
When Is Surgery Usually Considered?
Surgery is generally considered only when several important conditions are met:
- The source of traction has stopped or can be reliably eliminated.
- The diagnosis of traction alopecia has been confirmed.
- The hair loss is clinically stable rather than actively progressing.
- The affected area is permanently bald or significantly thinned and is unlikely to recover on its own.
- There is enough healthy donor hair for the planned restoration.
- The recipient scalp is suitable for graft placement.
- There is no evidence of active inflammation or another untreated scalp disorder.
- The patient understands that density may be limited and additional procedures may sometimes be discussed.
There is no universally validated waiting period that applies to every patient with traction alopecia. The appropriate timing depends on the cause, duration and pattern of hair loss, the condition of the scalp, and whether the disease has remained stable. A physician may recommend observation before surgery to confirm that progression has stopped.
Permanent loss versus recent thinning
Recent thinning after tight styling should not automatically be treated with surgery. Early traction alopecia may stabilize or partially improve after the pulling force is removed. Operating too early could mean treating an area that still has potential for natural recovery, while failing to address ongoing damage.
Transplantation is more relevant when the loss has become longstanding, cosmetically significant and unlikely to recover. A clinical examination is necessary to distinguish permanent follicular destruction from temporary or reversible thinning.
How Is Candidacy Assessed?
Medical history and examination
The physician will usually ask about hairstyles, extensions, headwear, hair-care practices, scalp symptoms and the duration of the hair loss. The distribution of thinning can provide useful clues. A detailed history may also help distinguish traction alopecia from other causes of hair loss that can affect the hairline or scalp.
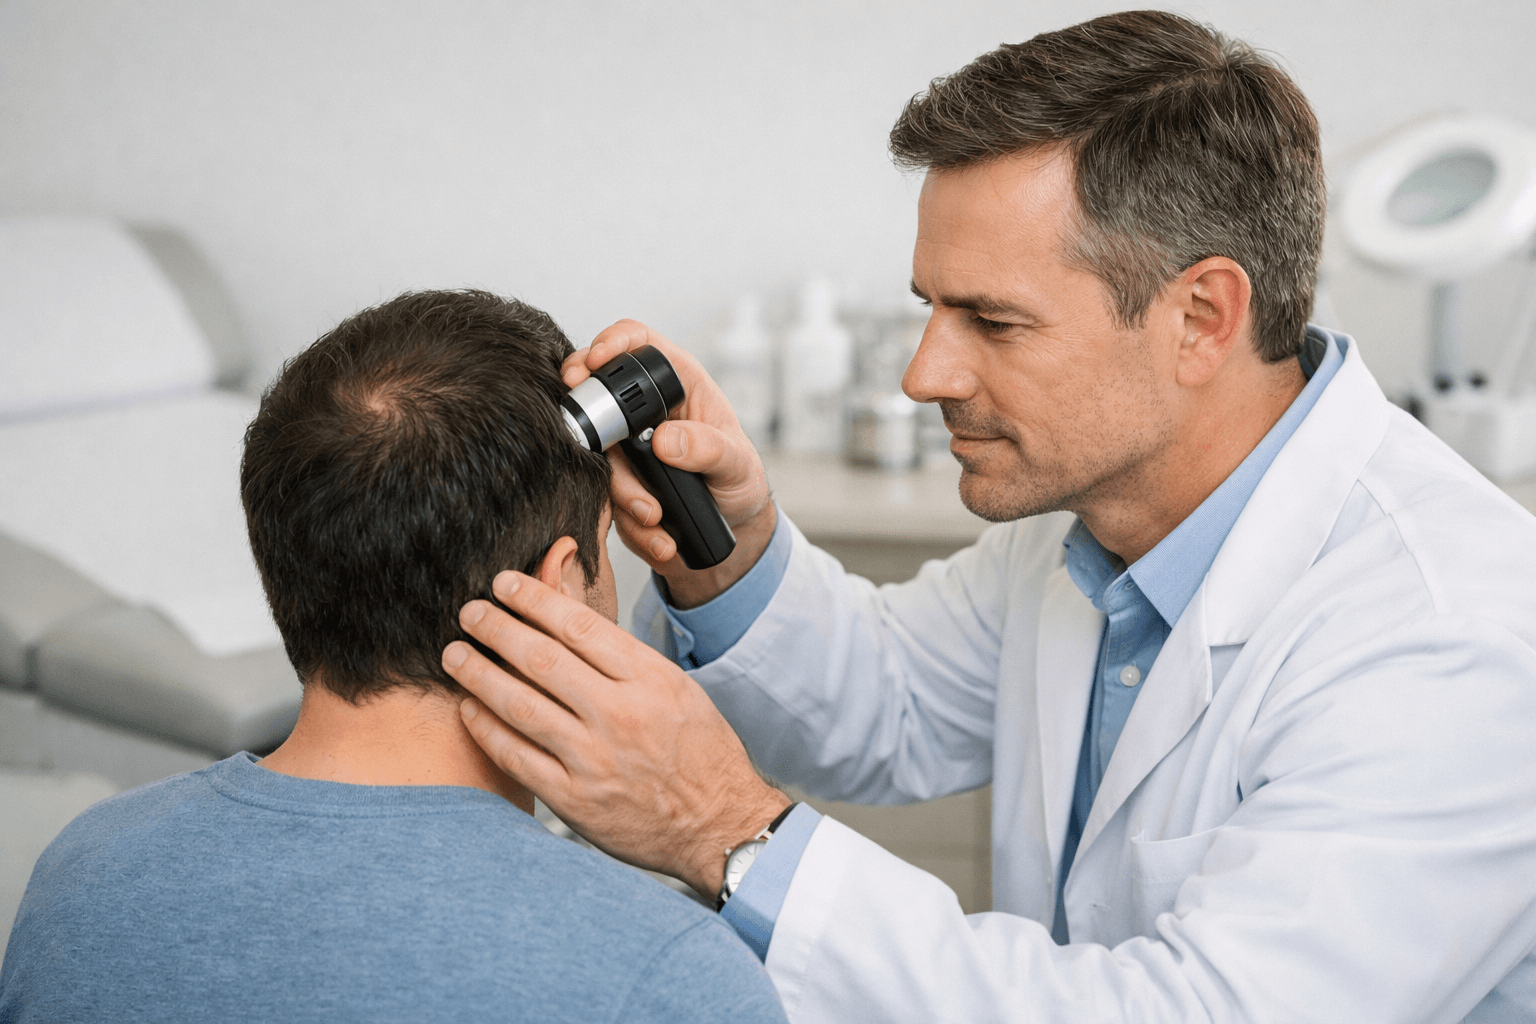
The scalp is examined for signs such as reduced follicular openings, smooth or shiny skin, broken hairs, tenderness, redness or scaling. The so-called fringe sign, in which some hairs remain at the very front of the hairline, may support the clinical assessment, but no single sign should be considered diagnostic in every patient.
Dermoscopy and biopsy
Dermoscopy can provide additional information about the follicles and scalp surface. It may help the clinician assess whether the pattern is more consistent with traction alopecia or another condition. If the diagnosis is uncertain, or if there are concerns about active inflammation or scarring, a scalp biopsy may be recommended.
Confirming the diagnosis is particularly important before surgery. Some inflammatory or scarring alopecias can resemble traction alopecia, and transplantation into an active disease process may produce an unpredictable outcome or be followed by renewed hair loss.
Donor hair and recipient-site evaluation
Adequate healthy donor hair is an essential part of planning. The physician must assess the density and quality of the donor area and consider how much can be used without creating visible thinning there. The recipient area is also evaluated for the degree of scarring, skin quality and the design that can be achieved safely.
Scarred scalp can be more difficult to treat than nonscarred scalp. Fibrosis and altered blood supply may affect graft placement and survival, making the result less predictable. This does not automatically rule out surgery, but it does make careful patient selection and realistic expectations especially important.
Preparing for a Hair Transplant
Preparation begins with removing the cause of traction. Patients should discuss their usual hairstyles and whether they can maintain low-tension hair practices after surgery. If the source of pulling continues, the risk of further hair loss remains.
Before an operation, the physician should establish whether the alopecia is stable and whether there is any active inflammation. The consultation may include dermoscopy, photographs for comparison and, when needed, biopsy. The doctor should also explain the expected level of coverage, the limits imposed by the donor supply and the possibility that more than one procedure could be considered in the future.
Patients travelling for treatment should understand what assessment will take place before surgery, who will perform it, and what follow-up arrangements are available after treatment. A remote review may help with initial planning, but an in-person evaluation is important before treatment is confirmed.
What Happens During the Procedure?
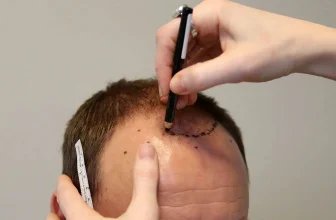
The exact surgical plan depends on the donor area, the size and location of the permanent loss, the condition of the recipient skin and the physician’s assessment. Hair follicles are harvested from a healthy donor region and prepared for placement in the affected area. The design should account for the natural direction and appearance of the existing hair, while using donor resources conservatively.
Scarred tissue may require a more cautious approach because its structure and vascularity differ from healthy, nonscarred scalp. The physician may explain that graft survival and final density are less predictable in such areas. The treatment plan should therefore prioritize a natural appearance and responsible use of the available donor hair rather than promising complete restoration.
Recovery and Aftercare
Aftercare instructions are individualized and should be followed closely. They may cover how to protect the recipient area, how to care for the donor site, when to resume particular hair practices and how to attend follow-up examinations. Patients should avoid returning to hairstyles that create strong or prolonged traction.
Follow-up is especially valuable when transplantation has been performed in a scarred area. The physician can assess healing, monitor the transplanted region and look for signs of renewed inflammation or progression. Patients should contact their treating clinic if they develop unexpected symptoms or have concerns during recovery.
The appearance of the hair may change during healing, and the final assessment should be made according to the physician’s guidance. Because the evidence for traction alopecia surgery is limited, recovery and visible improvement can vary between individuals.
Risks and Limitations
Hair transplantation for traction alopecia has several important limitations. The main concern is that graft survival may be less predictable in scarred tissue. Fibrosis and impaired vascularity can make the recipient area technically more challenging than healthy scalp.
There is also a risk that hair loss may continue if traction has not truly stopped or if the original diagnosis was incomplete. Disease relapse or progression is a recognized concern in the broader literature on transplantation for scarring alopecia. A transplant cannot protect untreated native hairs from ongoing mechanical damage.
Other limitations include a finite donor supply, restricted achievable density and the possibility that a repeat procedure may be discussed. No clinic can guarantee a particular cosmetic result. A qualified physician should explain the expected benefits, uncertainties and alternatives before consent.
When May Surgery Not Be Suitable?
Surgery may not be appropriate when traction is ongoing, the hair loss is still progressing, the diagnosis is uncertain or there are signs of active inflammation. It may also be unsuitable when the donor area does not contain enough healthy hair to meet the patient’s goals or when expectations are not realistic.
Patients who are hoping to continue tight hairstyles without further risk should discuss this honestly during consultation. The long-term protection of existing and transplanted hair is an important part of treatment planning. If the scalp is still exposed to repeated tension, restoration surgery cannot be considered a complete solution.
Key Questions to Ask Your Doctor
- Is the diagnosis definitely traction alopecia, or is further testing needed?
- Does the hair loss appear permanent and stable?
- Are there signs of active inflammation or another scalp condition?
- Is my donor area strong enough for the proposed restoration?
- How might scarring affect graft survival and density?
- What level of coverage is realistic?
- What changes to my hairstyles and hair-care routine will be needed?
- What follow-up will be available, particularly if I am travelling internationally?
Conclusion
A hair transplant may be suitable for carefully selected patients with permanent and stable traction alopecia. The most important steps are to stop the pulling force, confirm the diagnosis, establish that progression has ceased and evaluate both donor hair and recipient scalp quality.
Because transplantation in scarred tissue can be less predictable and the evidence specific to traction alopecia remains limited, treatment should be approached as individualized reconstruction rather than a guaranteed cure. A qualified physician can determine whether surgery is appropriate and explain what result may realistically be achieved.
Medical References
- Traction alopecia: the root of the problem. Clinical, Cosmetic and Investigational Dermatology; University of Miami authors; indexed in PubMed and available through PMC.
- Traction Alopecia. JAMA Dermatology.
- A Systematic Review of the Outcome of Hair Transplantation in Primary Scarring Alopecia. International Journal of Trichology.
- The Role of Hair Restoration Surgery in Primary Cicatricial Alopecia. International Journal of Women’s Dermatology.
- Extensive traction alopecia attributable to ponytail hairstyle and its treatment with hair transplantation. Dermatologic Surgery.