Written by: Estexper Medical Editorial Team
Medically reviewed by: Kafkas Celik, MD
Choosing between sleeve gastrectomy and Roux-en-Y gastric bypass involves more than comparing weight-loss procedures. If you have had kidney stones, the operation’s potential effects on urine chemistry and future stone risk should be part of the discussion.
In Short
For people with a history of kidney stones, current comparative evidence generally suggests that sleeve gastrectomy has a lower postoperative stone risk than Roux-en-Y gastric bypass. Bypass is more strongly associated with changes such as increased urinary oxalate and reduced urinary citrate, which may promote calcium oxalate stone formation. However, the most appropriate procedure depends on individual factors including stone history, kidney function, metabolic evaluation, and overall bariatric needs.
What is the difference between sleeve gastrectomy and gastric bypass?
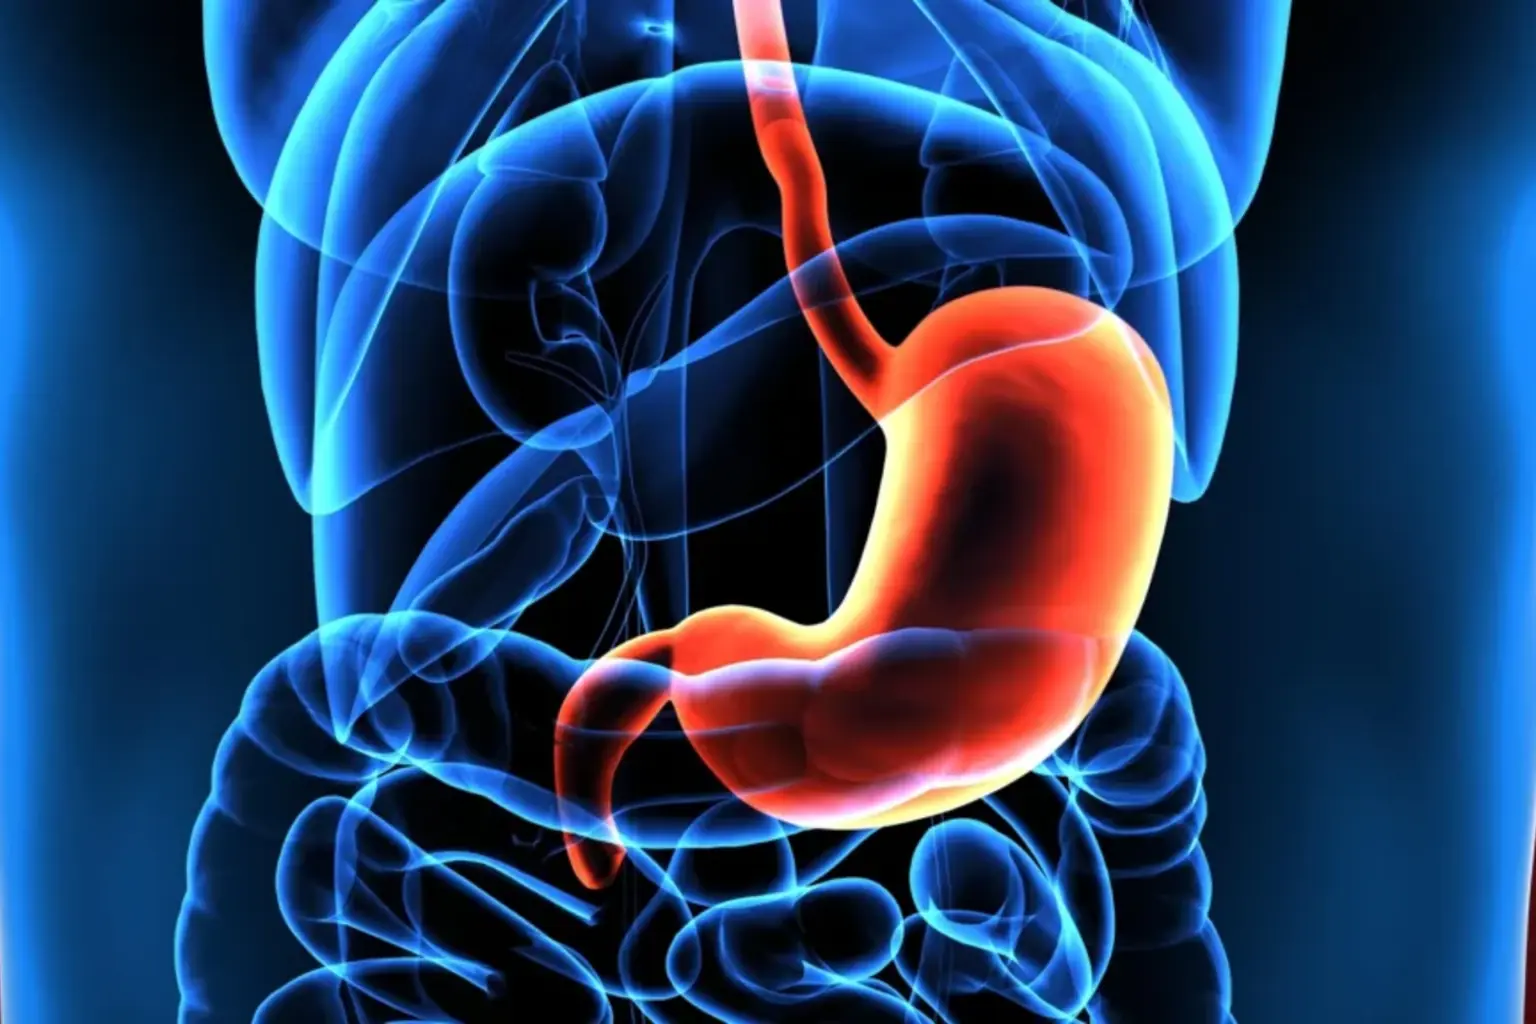
Sleeve gastrectomy reduces the size of the stomach by removing a substantial portion of it, leaving a narrow stomach sleeve. It is generally considered a restrictive bariatric procedure because it primarily limits meal capacity. The normal route through the small intestine is maintained.
Roux-en-Y gastric bypass creates a smaller stomach pouch and reroutes food around part of the small intestine. This can affect nutrient absorption and intestinal handling of certain substances, including oxalate. That malabsorptive component is important when evaluating kidney-stone risk.
Both procedures can produce significant weight loss and may improve obesity-related health problems, but they do not have identical effects on digestion, nutrition, and urinary chemistry. The most appropriate choice for a patient with previous stones depends on the complete clinical picture rather than stone history alone.
Which procedure is generally safer for people with previous kidney stones?
For kidney-stone risk specifically, current evidence generally favors sleeve gastrectomy over Roux-en-Y gastric bypass. A 2023 population-based comparative study found a higher incidence of nephrolithiasis after bypass than after sleeve gastrectomy at three months, six months, and one year. After adjustment for relevant factors, bypass remained associated with greater risk.
Another retrospective study of 1,802 patients reported symptomatic postoperative nephrolithiasis in 8.12% of patients after laparoscopic Roux-en-Y gastric bypass compared with 3.68% after sleeve gastrectomy. The study also found that a previous history of nephrolithiasis was a strong predictor of postoperative stones.
Research focused specifically on 102 patients with a history of nephrolithiasis provides additional context. At one year, patients who underwent gastric bypass had increased urinary oxalate and decreased urinary citrate. Patients who underwent sleeve gastrectomy generally had decreased urinary oxalate and stable citrate. Stone-burden progression and stone procedures were numerically more frequent after bypass, although these differences were not statistically significant.
These findings do not prove that every patient with prior stones will develop stones after bypass or that sleeve gastrectomy eliminates the risk. They do indicate that, when kidney-stone risk is an important factor and other indications are similar, sleeve gastrectomy may be the more kidney-stone-conscious option.
Why can gastric bypass increase kidney-stone risk?
The main concern after Roux-en-Y gastric bypass is enteric hyperoxaluria. In simple terms, more oxalate may be absorbed from the intestine and then excreted in the urine. This can increase the likelihood of calcium oxalate crystal formation.
Research and systematic reviews have associated gastric bypass with increased urinary oxalate, higher calcium oxalate supersaturation, and reduced urinary citrate or urine volume. These changes can make the urinary environment more favorable to stone formation. Lower urine volume may also mean that stone-forming substances are less diluted.
Hydration can be challenging after bariatric surgery, particularly during early recovery, because patients need to adapt to smaller meal and fluid volumes. Changes in food intake and altered intestinal absorption may also influence urine chemistry. The individual effect varies, so the risk should be assessed rather than assumed.
Sleeve gastrectomy does not create the same intestinal bypass. Its effect on kidney-stone risk is therefore generally less concerning in the available studies. Nevertheless, dehydration and dietary changes can still increase stone risk after any bariatric procedure, making prevention and follow-up important.
Does a previous kidney stone automatically rule out gastric bypass?
No. A history of kidney stones does not automatically make gastric bypass inappropriate. Some patients may have medical or metabolic reasons why bypass is considered, and the decision must balance its potential benefits against its risks. The type and severity of obesity-related disease, previous abdominal surgery, kidney function, current medications, and the pattern of stone disease may all affect suitability.
However, previous nephrolithiasis should not be treated as a minor detail. It is a recognized predictor of postoperative stone formation, and recurrent stones may justify a more detailed assessment before surgery. The clinical team may need to understand:
- How many stone episodes you have had and when they occurred
- Whether a stone was analyzed and what it contained
- Whether imaging shows current stones or residual stone burden
- Whether you have had urinary infections, obstruction, or stone procedures
- Your kidney function and relevant blood-test results
- Your dietary pattern, fluid intake, and family history
Patients with recurrent or high-risk stones may benefit from metabolic evaluation, including a 24-hour urine collection. The American Urological Association identifies malabsorptive bariatric surgery as a cause of enteric hyperoxaluria and recommends metabolic evaluation for patients at increased risk of stones.
What should be checked before bariatric surgery?
Before deciding between sleeve gastrectomy and gastric bypass, provide your bariatric team with complete information about your kidney-stone history. Bring previous imaging reports, stone-analysis results, laboratory results, and a list of treatments or procedures related to stones if these are available.
A physician may consider blood testing, kidney-function assessment, urine testing, and imaging based on your history. For recurrent or complicated stone disease, a 24-hour urine evaluation can help identify factors such as oxalate, citrate, urine volume, and other markers relevant to prevention. The exact testing plan should be individualized.
It is also important to discuss why each bariatric procedure is being considered. The choice should not be based solely on which operation appears to have a lower stone rate. A qualified surgeon should assess overall suitability, while a urologist or nephrologist may provide additional guidance when stone risk is recurrent, severe, or associated with impaired kidney function.
How can kidney-stone risk be reduced after surgery?
Prevention after bariatric surgery should be planned with your clinical team. Adequate fluid intake is one of the central principles, but the appropriate daily target and drinking pattern should be tailored to your postoperative stage and medical condition. Small, frequent sips may be easier to tolerate than large drinks, especially during early recovery.
Dietary calcium may also be important when enteric hyperoxaluria is present. American Urological Association guidance emphasizes appropriate calcium taken with meals to reduce intestinal oxalate absorption, but supplementation should be individualized. Do not begin calcium, citrate, or other supplements without discussing the dose and timing with your bariatric team or another qualified clinician.
Follow your postoperative nutrition plan carefully and attend scheduled appointments. Supplements and laboratory monitoring should be managed by the treating team. Report symptoms such as severe flank pain, blood in the urine, fever, vomiting, or difficulty urinating promptly, as these may require urgent medical evaluation.
Recovery and follow-up considerations
Recovery varies between individuals and depends on the operation, general health, and the surgeon’s protocol. After either procedure, the early diet usually progresses gradually according to clinical instructions. Hydration can be challenging during this period, so patients should follow the prescribed drinking plan and contact their team if they cannot keep fluids down.
For patients with previous stones, follow-up should address more than weight loss. The clinical team may review fluid intake, dietary tolerance, kidney function, urinary symptoms, and the need for repeat urine testing or imaging. Those who undergo gastric bypass may require especially careful attention to oxalate, citrate, and urine volume if their history or test results suggest increased risk.
International patients travelling to Turkey should arrange a clear follow-up plan before returning home. Ask which medical records will be provided, when laboratory or imaging checks should occur, who to contact with postoperative concerns, and how your local doctor can coordinate with the surgical team. Follow-up with a local urologist, nephrologist, or bariatric physician may be appropriate depending on individual needs.
Potential risks and limitations of the evidence
The available research supports a lower kidney-stone risk after sleeve gastrectomy compared with Roux-en-Y gastric bypass, but important limitations remain. Much of the evidence is observational rather than based on randomized trials. Study populations, follow-up periods, dietary practices, and definitions of postoperative nephrolithiasis may differ.
Some studies have also grouped sleeve gastrectomy with other restrictive procedures, making direct comparisons less precise. A higher risk after bypass does not mean that complications are inevitable, and a lower risk after sleeve does not guarantee that stones will not occur.
There may also be reasons to recommend one operation for broader medical or surgical indications. The final decision should therefore consider weight-loss objectives, obesity-related conditions, kidney function, the composition and recurrence pattern of stones, nutritional requirements, and the patient’s ability to follow hydration and monitoring instructions.
Questions to ask your bariatric team
- How does my personal stone history affect the choice between sleeve gastrectomy and gastric bypass?
- Should I have a 24-hour urine test or additional kidney evaluation before surgery?
- Do my stone-analysis results suggest a higher risk after a malabsorptive procedure?
- How will I maintain hydration after surgery?
- Should calcium be taken with meals, and what dose is appropriate for me?
- What symptoms should prompt urgent medical attention?
- What follow-up will be available if I return home after treatment in Turkey?
Bottom line
For patients with a previous history of kidney stones, sleeve gastrectomy generally appears to carry a lower nephrolithiasis risk than Roux-en-Y gastric bypass. Comparative studies show higher stone incidence after bypass, and research in previous stone formers suggests that bypass may worsen urinary oxalate and citrate profiles.
Even so, the most appropriate bariatric procedure cannot be selected from a single risk factor. A qualified physician should review kidney function, stone composition, recurrence history, metabolic results, weight-loss goals, and other medical needs. With appropriate preoperative evaluation, hydration guidance, nutrition support, and coordinated follow-up, the treatment plan can be tailored to the individual patient.
Explore our Bariatric Surgery services in Turkey for an overview of treatment options and individual assessment.
TREATMENT OPTIONS
Explore Your Treatment Options
Find out more about our services and discuss which options may suit your individual needs.
YOUR NEXT STEP
Discuss Your Questions With Our Team
Request an individual assessment or ask our team about treatment planning and follow-up arrangements.
Medical References
- Incidence of Kidney Stones After Bariatric Surgeries: Comparing Roux-en-Y Gastric Bypass and Sleeve Gastrectomy. Journal of Gastrointestinal Surgery; PubMed.
- Nephrolithiasis after bariatric surgery: A comparison of laparoscopic Roux-en-Y gastric bypass and sleeve gastrectomy. The American Journal of Surgery; PubMed.
- Bariatric Surgery in Patients with a History of Nephrolithiasis: 24-h Urine Profiles and Radiographic Changes After Roux-en-Y Gastric Bypass Versus Sleeve Gastrectomy. PubMed.
- Risk of nephrolithiasis, hyperoxaluria, and calcium oxalate supersaturation increased after Roux-en-Y gastric bypass surgery: a systematic review and meta-analysis. PubMed.
- Medical Management of Kidney Stones: AUA Guideline (2026) Part I: Evaluation of Patients With Kidney Stones and Dietary Management of Patients With Calcium Stones. American Urological Association; Journal of Urology.